What Is Cord Blood Banking and How Does It Work
Stem cells in newborn cord blood can treat dozens of serious diseases.
Cord blood banking is the practice of collecting blood from a newborn's umbilical cord right after birth and freezing it for possible medical use later. It works because that blood holds a concentrated supply of stem cells capable of treating dozens of serious diseases, and because the window to collect it closes within minutes of delivery, understanding the biology and the logistics ahead of time is what lets parents make a real decision rather than a rushed one.
Cord blood and why it would otherwise be discarded
For most of medical history, the blood left behind in the umbilical cord and placenta after birth went straight into a biohazard bin. What changed is the recognition that this leftover blood carries a dense population of hematopoietic stem cells, the cells responsible for producing every type of blood cell the body uses: red cells, white cells, platelets. These are the same stem cells found in bone marrow, only younger and, by most clinical measures, more potent.
That youth matters clinically. That single fact widens the pool of people a given unit could help, which is part of why cord blood has become a distinct category of medical resource rather than a bone marrow substitute.
Parents enrolling in a banking program will often see two options presented side by side: cord blood and cord tissue. They are not the same thing. Cord blood contains hematopoietic stem cells, tied to the blood and immune system, while cord tissue contains mesenchymal stem cells, which are involved in forming muscle, bone, and cartilage. Some banks collect both, some only one, an important distinction to know before signing any paperwork.
Collection happens after the cord is already clamped and cut, so it poses no danger to the mother or the baby, a point the Cleveland Clinic makes. ACOG adds an important qualifier: the process should never be allowed to interfere with the obstetric or neonatal care already underway, and parents should understand upfront that private storage carries ongoing costs. Safety at the point of collection doesn't mean the entire arrangement is cost-free. ACOG notes that cord blood cells require less precise HLA matching than adult donor cells.
What cord blood stem cells can treat today
The clearest, most established use of cord blood is rebuilding a blood and immune system wiped out by disease itself or by the chemotherapy used to treat it. This is established medicine, and it's been standard practice for years across a defined set of conditions.
According to the Cleveland Clinic and ACOG, cord blood stem cells treat blood cancers such as leukemia and lymphoma, bone marrow failure syndromes, blood disorders including sickle cell anemia and Diamond Blackfan anemia, immune system disorders, certain inherited genetic conditions, and select metabolic disorders. Taken together, industry sources put the number of treatable conditions above 80. That's a wide net for a substance that used to be thrown away.
Compared with bone marrow, cord blood carries real clinical advantages. ACOG notes a lower risk of graft-versus-host disease, a serious complication where transplanted cells attack the recipient's body, along with greater tolerance for HLA mismatch and the practical benefit of being ready to use immediately, whereas bone marrow generally has to be transplanted soon after it's collected. Survival data backs up the clinical promise: published research cited by PubMed Central and ACOG puts overall survival at 60 to 70 percent in pediatric transplant recipients and 55 to 65 percent in adults PMC / PubMed Central. Those numbers aren't guarantees, but they represent a meaningful chance for patients who often have few other options.
The FDA has formally licensed a handful of cord blood products for specific uses, including ALLOCORD, CLEVECORD, Ducord, HEMACORD, and REGENECYTE, with more than five licensed products in total as of December 2025. FDA approval applies to those specific products, not to cord blood banking as a general practice.
One distinction trips up a lot of parents early on: autologous versus allogeneic use. Autologous means using a child's own banked cord blood on that same child, and ACOG notes this is actually rare, because when the condition being treated is genetic, the child's own cells carry the identical defect. Allogeneic use, where the cord blood goes to a sibling or another matched patient, is far more common in practice. That single fact reframes what "banking for your child" actually means in most real cases: it's often banking for a family rather than a single individual.
A documented case from ViaCord illustrates the allogeneic pathway well. A pediatrician named Kathy banked her eldest son Andrew's cord blood at birth. Years later, her second son Luke was born with Diamond Blackfan anemia, and Andrew's banked cord blood ended up providing the stem cells for a transplant that gave Luke a real shot at recovery. Luke is reported to be thriving today.
Beyond established transplant medicine, researchers are running clinical trials looking at cord blood in regenerative contexts, including cerebral palsy, brain injury, cardiac conditions, hearing loss, autism, and diabetes, unproven treatments still under active investigation. It's active investigation, and framing it as anything more settled than that would be dishonest to the current state of the science.
How collection works from late pregnancy through delivery
The decision-making needs to happen well before labor starts, not during it. Private banks generally require enrollment and payment finalized before delivery day arrives.
Consent looks different depending on the path chosen. Public donation requires consent to begin before labor starts. Private storage requires a signed contract, paid fees, a maternal health history, and consent to infectious disease testing, all handled ahead of time.
For families going the private route, the bank ships a collection kit to the parents in advance, since private banks aren't affiliated with specific hospitals the way public donation programs sometimes are. That kit travels with the parents to the hospital on delivery day.
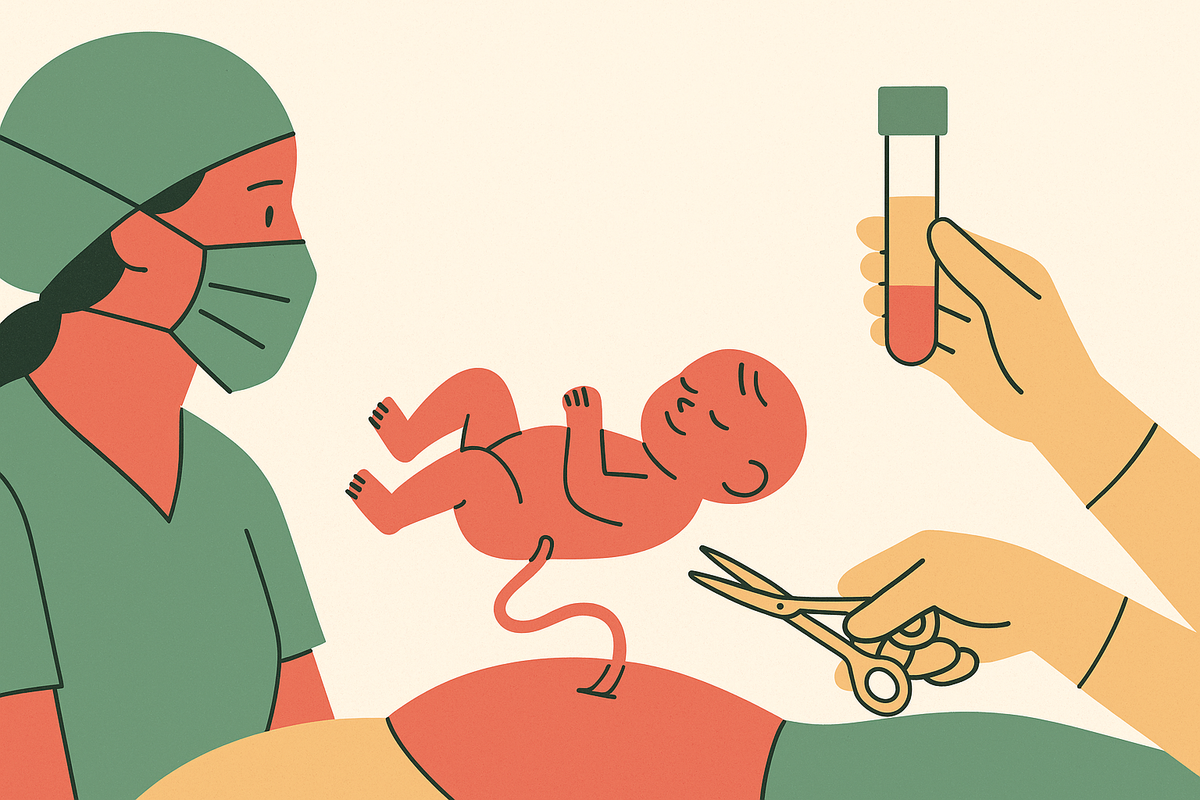
The collection itself is quick. According to ACOG, it's performed by the OB or hospital staff immediately after the cord has been clamped and cut. A needle draws the residual blood from the cord into a collection bag, and the whole thing takes roughly 5 to 10 minutes, described as safe and painless for both mother and baby Banking Your Baby's Cord Blood: Benefits, Process, and Costs. It works with a cesarean birth just as it does with vaginal delivery, and it's compatible with a delayed cord clamping plan, though delaying the clamp does reduce the volume of blood available to collect.
Sometimes there simply isn't enough to bank. Preterm birth, delayed clamping, or an emergency during delivery can all result in insufficient volume, and parents should go in knowing that's a real possibility, not a hypothetical one.
Once collected, a qualified unit gets processed and cryopreserved within 48 hours. The clock starts the moment the bag is filled. Cells4Life's patented TotiCyte technology reportedly delivers 3x more viable stem cells at point of therapy than industry-standard processing, meaning even smaller samples collected after delayed cord clamping may yield comparable cell counts, illustrating that processing method matters alongside collection volume.
How cord blood is processed and stored after collection
Not every sample that gets collected ends up banked. Units need to clear a minimum threshold for volume and cell count before they qualify for long-term storage, and units that fall short simply don't get banked, regardless of the family's intent.
In the lab, the cord blood unit goes through a process to isolate and concentrate its stem cells, and the specific method used varies from bank to bank, which in turn affects how many viable cells come out the other end. This is one of the least visible parts of the whole arrangement to parents, yet it's arguably where the value of a private bank's promise actually gets decided.
Cells are frozen and stored at –150°C (–238°F) Banking Your Baby's Cord Blood: Benefits, Process, and Costs.
What happens after freezing depends entirely on which path the family chose. Public bank units get listed on a searchable registry, such as the one maintained by the NMDP, making them available to transplant centers anywhere in the world and tracked electronically for fast retrieval. Private bank units, by contrast, are reserved exclusively for the depositing family and never appear on any public registry.
Testing runs in parallel with all of this. ACOG notes that the mother's blood gets tested for infections and genetic disorders, and the cord blood itself is tested after collection, with the results determining the unit's ultimate clearance for storage. A unit that fails this testing doesn't get banked, full stop.
The field keeps moving, too. Cryopreservation and processing methods keep evolving, with industry sources describing ongoing improvements to the quality and long-term viability of stored cells. What a bank offers today isn't necessarily what it offered five years ago, a factor to weigh into any long-term storage decision.
Public banking, private banking, and hybrid options compared
Public banks cost the donating family nothing. Not every hospital is equipped to collect for a public bank, though, so parents need to confirm ahead of time whether their delivery hospital participates.
There's a diversity dimension to public donation that deserves attention. As of 2025, 53 percent of the cord blood units on the NMDP registry came from ethnically diverse donors, which matters directly for minority families searching for a match. A more diverse registry means a better shot at finding a compatible unit, and that's a systemic benefit that individual private banking simply can't replicate.
Private banks work on a different model. The unit is reserved exclusively for the depositing child or a family member, and private banks aren't regulated by the FDA in the same way public banks are. Despite the cost, private banking dominates the market: Coherent Market Insights reports it captures roughly 57 percent of the global cord blood banking market. Private storage tends to make the most sense when a sibling already has a condition treatable with stem cells, or when there's a documented family history of blood cancer, sickle cell disease, or a rare immune disorder.
A middle path exists, too. Under hybrid banking, a family stores cord blood privately at first, and if it goes unused, it can later be donated to a public bank. Some of these programs charge little to no fee, and they've become more widely available heading into 2026. There's also directed donation, a lesser-known option where a public bank will store cord blood specifically for a family that has a member with a condition treatable by stem cells, blending the no-cost structure of public banking with the targeted intent of private storage.
Families weighing private storage should judge providers less on marketing and more on the fundamentals: processing quality, accreditation, storage conditions, and a track record of documented outcomes, the kind reflected in cases like Luke's. Those factors, not brand recognition, make a stored unit actually usable decades down the road. The family pays an initial collection fee plus annual storage fees, with a typical cost range of $2,500–$3,500 My Medicine Advisor.
What medical organizations say about who should bank privately
The major medical bodies are fairly unified on this question.
The AMA states that private banking is worth considering only in the "unusual circumstance when there exists a family predisposition to a condition in which umbilical cord stem cells are therapeutically indicated." Cost, the low likelihood of ever using the unit, and the fact that a privately stored unit is inaccessible to anyone outside the family are all cited as reasons not to recommend it as a general practice. UnitedHealthcare's coverage policy reflects the same skepticism, classifying prophylactic collection and storage for a currently healthy person as unproven and not medically necessary.
The math behind that caution is straightforward. The likelihood that a privately banked unit ever gets used is characterized as relatively low across the general population, and the autologous case is further narrowed by the genetic reality already discussed: a child's own cells can't treat that child's own genetic disease or that child's own leukemia, since the defect lives in the cells themselves. Ethicists studying the industry raise additional concerns around private versus public ownership of stored units, fair access, the adequacy of informed consent processes, confidentiality, and potential conflicts of interest when the founders of a bank are also its clinicians.
There's a diversity gap tangled up in all of this, too. That's a structural problem, not something any single family's decision can fix on its own.
None of this amounts to a blanket "don't bank privately." The guidance carves out a clear exception: families with an identified medical risk, or a sibling already affected by a treatable condition, are specifically named as reasonable candidates for private storage. It's against private banking as a default for families with no elevated risk.
The policy and market context shaping access and cost
Cost has become a live policy question as well as a personal budgeting one. H.R.2810, the Family Cord Blood Banking Act, was introduced in the 119th Congress on April 10, 2025. It's currently sitting with the House Committee on Ways and Means and remains, as of this writing, introduced and not yet law.
If it passes, the bill would amend the Internal Revenue Code to classify payments for private cord blood or cord tissue banking as medical care expenses, making them eligible for medical expense deductions. That treatment would apply specifically to accredited banks complying with Public Health Service Act regulations. In plain terms, it would make private banking meaningfully cheaper for families who qualify, though it changes nothing about the underlying clinical odds of ever using a stored unit.
The market backing all of this is large by any measure, even if the exact size depends heavily on who's counting and how. The Business Research Company put the global market at $28.57 billion in 2025, projecting growth to $39.7 billion by 2030 at a 6.8 percent annual rate Straits Research. Straits Research arrived at a far smaller figure, $2.29 billion in 2025, with a steeper 13.8 percent annual growth rate through 2034 The Business Research Company.
Mordor Intelligence reports that within that market, cancer treatment represented 37.67 percent of applications in 2025, while metabolic disorders are the fastest-growing segment, expanding at a 10.32 percent annual rate through 2031. Geographically, North America led with a 39.54 percent share in 2025, though Asia-Pacific is projected to grow fastest, at 8.24 percent annually through 2031 Mordor Intelligence.
Regulatory momentum is building alongside the market. The FDA's December 2025 approval of Omisirge, an ex-vivo expanded cord blood product, for severe aplastic anemia removes longstanding dose limitations that once constrained how cord blood could be used clinically, and it's expected to increase physician confidence in cord blood transplants more broadly. For a family weighing this decision right now, three forces are all moving at once: the real cost of private storage, a pending policy shift that could ease that cost, and a clinical field whose usable applications keep expanding. None of those three are static, and that is why the decision resists a one-size-fits-all answer.
Deciding Before the Due Date
Timing drives everything here. Waiting until the third trimester to even start thinking about it is already cutting things close.
A handful of questions tend to separate families who belong in the private-banking exception from those better served by public donation. Does the family carry a known history of blood cancer, sickle cell disease, an immune disorder, or a metabolic condition? Is there a child or close relative currently in need of a stem cell transplant? Does the delivery hospital even collect for a public bank, and is the family eligible to participate? Is the family part of a group underrepresented in current public registries, where donating would serve a broader need beyond their own household? And, practically, can the family sustain the ongoing storage fees for years, potentially decades, without strain?
Whatever the answers turn out to be, a few steps apply no matter which direction a family leans. Bring it up with the OB-GYN at a prenatal visit, not after labor has already begun. Confirm directly what the delivery hospital is actually equipped to do when it comes to public collection. If private storage is the choice, compare accredited banks on processing technology, storage conditions, and fee structure rather than on advertising alone. Then complete the consent forms and, for private banking, finalize enrollment well before the due date arrives, so that when the moment comes, and it only comes once, there's nothing left to decide. ACOG recommends securing a collection kit at least 6 weeks before the due date, while Cleveland Clinic advises deciding by around 34 weeks.
Sources
- Cord Blood Banking: Benefits, Process & What To Expect
- Cord Blood Banking | ACOG
- Text - H.R.2810 - 119th Congress (2025-2026): Family Cord Blood Banking Act | Congress.gov | Library of Congress
- Cord Blood Banking: The Ultimate Guide for Parents (2026)
- Banking Your Baby's Cord Blood: Benefits, Process, and Costs
- Umbilical cord blood: a comprehensive review of protective and restorative properties in clinical applications – a narrative review - PMC
- Cord Blood Donation Process: From Birth to Donating | NMDP
- Cord Blood Banking: Worth It or a Costly Mistake?